How the Anion Gap Measures in DKA
The anion gap is a laboratory-derived value that helps identify the origin of metabolic acidosis. In diabetic ketoacidosis, it is especially useful because it indicates the accumulation of acids that are not directly measured on a standard chemistry panel. This renders the anion gap a useful diagnostic tool for recognizing high anion gap metabolic acidosis.
An anion gap calculator calculates the difference between the major measured cations and anions in the blood. The result helps clinicians review serum chemistry data in the context of the patient’s acid-base balance. In DKA, the gap elevates as ketones build up and contribute unmeasured anions to the bloodstream.
Because DKA is an acidotic state, the body typically shows a low bicarbonate level along with an elevated anion gap. That pattern reflects ketone accumulation and a wider metabolic derangement. The anion gap does not diagnose DKA by itself, but it helps reinforce the diagnosis and tracks how the condition is evolving over time.
How to Use an Anion Gap Calculator
An anion gap calculator relies on a few standard lab values from the electrolyte panel. You input the serum sodium, serum chloride, and serum bicarbonate values, and the calculator uses the calculator formula to generate the result.
The typical workflow is easy:
- Collect the latest serum sodium value. Record the serum chloride value. Obtain the serum bicarbonate value from the serum chemistry panel. Add the values into the calculator. Examine the result alongside the rest of the laboratory results and clinical assessment.
This is useful because DKA evaluation hardly ever depends on one number alone. The anion gap is part of a broader lab interpretation process that includes the patient’s symptoms, glucose level, ketone testing, pH, and treatment response. A calculator speeds up the math, but interpretation still demands clinical judgment.
Many clinicians use the result as a rapid screen for metabolic acidosis and as a marker of resolution of acidosis during treatment monitoring. As the underlying ketoacidosis improves, the anion gap should trend toward normal and eventually show anion gap closure.
Anion Gap Formula and Normal Ranges
The standard anion gap formula is:
Anion gap = Sodium − (Chloride + Bicarbonate)
By applying this formula, the calculator determines the relationship between measured ions in the blood. Sodium is the main measured cation, while chloride and bicarbonate are the main measured anions included in the equation. Any additional acids in the blood are often represented indirectly as unmeasured anions.
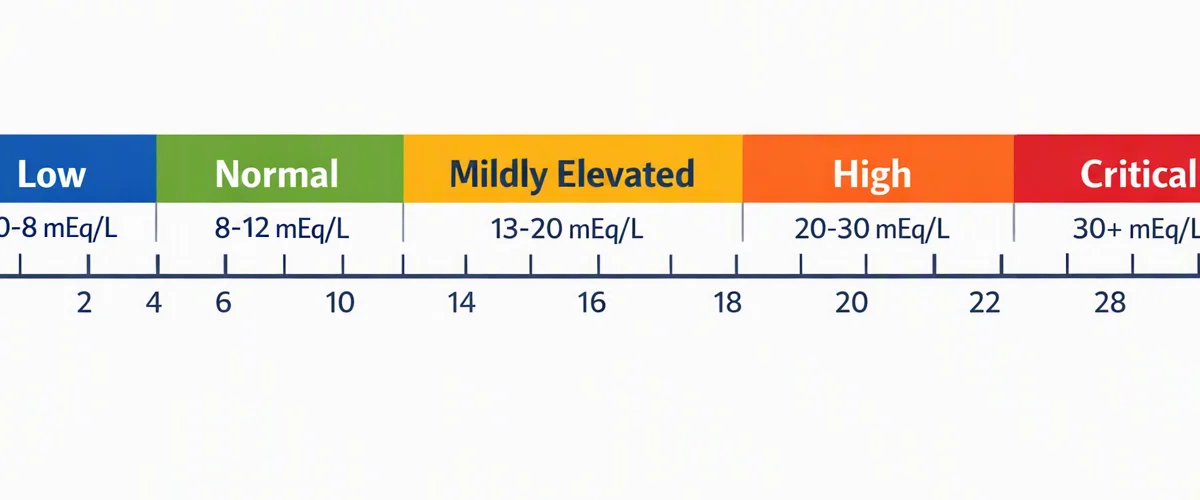
The normal anion gap range differs a bit depending on the laboratory method and the reference range used by that lab. That variation is why it is important to read the number in context rather than rely on a single universal cutoff. A mildly different result may still be normal if the lab’s reference interval differs.
In practice, the anion gap should be read with the rest of the electrolytes and with awareness of albumin correction. Albumin is a anion-like protein that affects the gap, so lower albumin can make the gap appear falsely low or normal. That is an important reason a raw value may not tell the full story.
Why the Anion Gap Is Raised in Diabetic Ketoacidosis
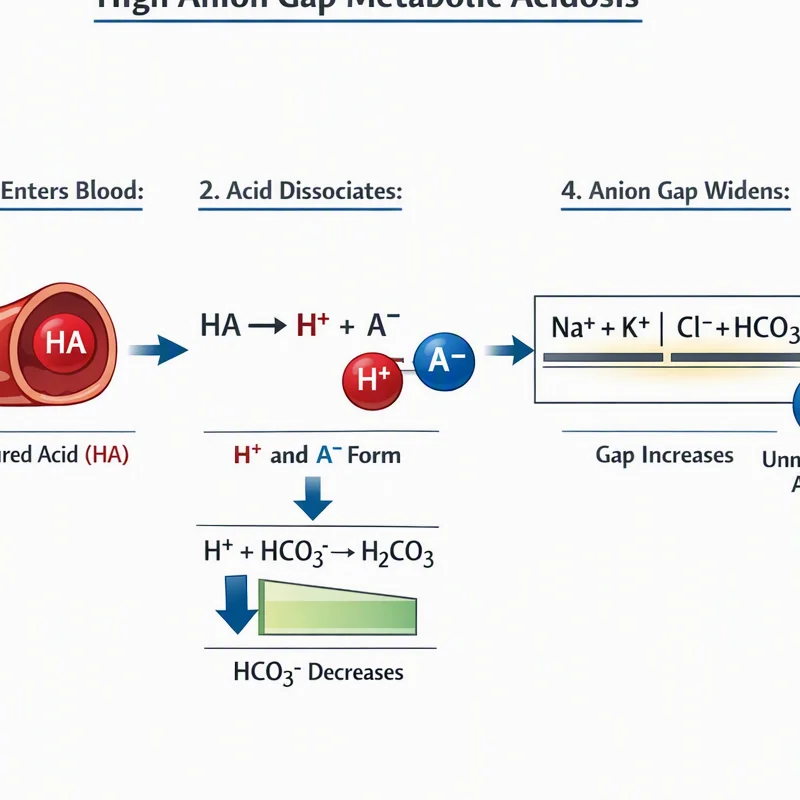
In DKA, insulin deficiency leads to greater fat breakdown and production of ketones, especially acetoacetate and beta-hydroxybutyrate. These acids add to the blood as unmeasured anions, which raises the anion gap and contributes to ketoacidosis.
The process is a straightforward disturbance in acid-base balance. As ketones pile up, they consume bicarbonate, decreasing the bicarbonate level and resulting in a metabolic acidosis with a high anion gap. This pattern is a recognizable hallmark of DKA and helps distinguish it from other forms of acidosis.
Beta-hydroxybutyrate is often the dominant ketone in severe DKA, so the degree of ketosis may be higher than a urine ketone test suggests. That is why the anion gap and direct ketone testing are complementary. Together, they describe the patient’s acid burden more precisely than either test alone.
Correcting the Anion Gap for low albumin
Albumin strongly influences the measured anion gap because it is a major unmeasured anion in blood. When albumin is low, the anion gap may be underestimated. This is why albumin correction is often recommended, especially when the clinical picture suggests acidosis but the raw gap seems less striking than expected.
Hypoalbuminemia can occur in many hospitalized patients and can mask a true high-gap process. In that setting, a corrected anion gap gives a better picture of the patient’s metabolic state. The corrected value helps avoid missing DKA or downplaying the degree of acid accumulation.
Although formulas for albumin correction can vary slightly, the goal is the same: correct the gap based on the measured serum albumin so the value better reflects the true acid burden. This matters because a normal-looking gap can be deceptive if albumin is low. In DKA workups, the corrected value can improve lab interpretation and support more precise treatment monitoring.
Other Labs to Assess Together with the Anion Gap
The anion gap is only one part of the DKA workup. A thorough evaluation also covers blood glucose, ketone measurement, and acid-base testing. These studies support the diagnosis of the diagnosis and guide management.
An arterial blood gas or venous blood gas can provide the pH and bicarbonate level, which show how severe the acidemia is. While venous testing is often adequate in many settings, the choice relies on the clinical context. Either way, the pH helps define the acidotic state and adds to the differential diagnosis.
Beta-hydroxybutyrate is especially valuable because it directly indicates ketone burden. It can verify ketone accumulation even when other markers are less clear. Blood glucose is also essential, but a normal or only mildly elevated glucose does not rule out DKA, especially in euglycemic presentations.
Reviewing these findings together creates a more complete picture of the metabolic derangement. The anion gap, blood gas, glucose, and ketones should be viewed as a group rather than as isolated laboratory results.
How the Anion Gap Changes During DKA Treatment
Management of DKA typically includes insulin therapy and intravenous fluids. As insulin inhibits ketone production and fluids improve circulation and renal clearance, the anion gap should steadily fall. This trend is one of the clearest signs that treatment is working.
During treatment monitoring, the clinician looks for anion gap closure, which suggests that the major ketoacid burden is clearing. The gap may normalize before the bicarbonate fully recovers, so it is important to look at the entire pattern rather https://anion-gap-values450.wpsuo.com/what-drugs-can-lead-to-high-anion-gap-metabolic-acidosis than one value alone.
Electrolyte monitoring is essential during this phase. Potassium, sodium, chloride, and bicarbonate can shift quickly as therapy progresses. IV fluids and insulin can also affect the apparent acid-base profile, so serial labs are needed to verify true improvement rather than a temporary lab shift.
As treatment continues, the goal is not only to stabilize glucose but also to correct the underlying acidosis. The anion gap helps show whether the ketoacid production has slowed and whether the body is progressing toward a stable acid-base balance.
Typical Pitfalls & Interpretation Errors
One common pitfall is not recognizing a combined acid-base disorder. A person with DKA may also have nausea and vomiting, problems with respiratory compensation, or another metabolic process that changes the expected pattern. In those cases, the anion gap may not fully explain the situation by itself.
Laboratory error is another issue. A single incorrect sodium, chloride, or bicarbonate result can skew the calculated gap and lead to misleading conclusions. If the number does not match the clinical picture, it is appropriate to run the test again and review the full electrolyte panel.
Hyperchloremic metabolic acidosis can develop during or after DKA treatment, especially after large volumes of chloride-containing fluids. This can lower the bicarbonate while the anion gap normalizes, making the metabolic picture look confusing. In that setting, the persistent acidosis may be due to chloride rather than ongoing ketone production.
Serum albumin also is important here. If albumin is low and not accounted for, the gap may appear falsely reassuring. Careful lab interpretation requires awareness of the corrected value, the clinical assessment, and the treatment timeline.
When a Normal Anion Gap Is Not Enough to Exclude DKA
A normal anion gap does not fully rule out DKA. One important example is euglycaemic DKA, where the blood glucose may be normal or only mildly elevated despite active ketoacidosis. This can happen in certain medication contexts or with reduced carbohydrate intake, and it requires a high index of suspicion.
Another reason the gap may seem normal is that beta-hydroxybutyrate can remain elevated even when other markers are less dramatic. In early or partially treated disease, the anion gap may also begin to improve before the full metabolic picture resolves. That is why bedside assessment is so important.
If the patient still has symptoms and there is ongoing acidosis on blood gas testing, DKA can still be present even when the gap is not clearly elevated. In that setting, the differential diagnosis should include DKA, mixed disorders, and other causes of acidosis. The anion gap is valuable, but it is not a standalone rule-out test.
FAQ
What is the anion gap in diabetic ketoacidosis?
In diabetic ketoacidosis, the anion gap is a calculated laboratory value used to identify elevated anion gap metabolic acidosis. The gap rises because ketones accumulate as unmeasured negative ions, decreasing bicarbonate and enlarging the gap. It is used to support diagnosis and follow improvement during treatment.
How do you calculate the anion gap from lab values?
Use the anion gap calculator or follow the calculation formula for the anion gap: sodium minus the sum of chloride and bicarbonate. The required values are serum sodium, serum chloride, and blood bicarbonate. Interpret the result together with the rest of the serum chemistry and clinical findings.
What is the normal anion gap range for adults?
A expected anion gap range depends on the laboratory’s normal range and testing method. Since ranges can differ, the best approach is to compare the result with the lab’s stated normal limits rather than relying on one universal number. Albumin level can also affect what looks normal.
What is the reason for correcting the anion gap for albumin?
Correcting the anion gap for serum albumin because low albumin can make the gap appear falsely low or normal. In low albumin, the measured value may underestimate the degree of acidosis. Correction for albumin helps produce a more accurate albumin-corrected anion gap for lab interpretation.
Is diabetic ketoacidosis possible with a normal anion gap?
Yes, it can. Euglycemic DKA, early treatment, low albumin, or a mixed acid base disorder can make the gap appear normal even when DKA is still present. If symptoms, ketones, pH, and bicarbonate point to ongoing disease, the diagnosis should still be considered even with a normal gap.