What the Anion Gap Is and Why It Is Important
The anion gap is a useful lab-calculated value used to detect the cause of metabolic acidosis and other imbalances in electrolytes. In the emergency department, it functions as a rapid screening tool for acid-base balance problems and helps clinicians focus a broad differential into a targeted diagnostic algorithm.
An anion gap calculator is helpful because the underlying concept is simple, but the interpretation is not. A patient may present with an apparently mild metabolic derangement, yet the pattern of serum electrolytes can reveal severe illness such as lactic acidosis, ketoacidosis, toxic ingestion, or renal failure. The gap represents the difference between measured cations and measured anions, which reflects unmeasured anions in the blood.
For emergency medicine, the anion gap is not just a number. It is a piece of clinical decision support that helps identify whether the patient likely has high anion gap metabolic acidosis, normal anion gap metabolic acidosis, or another acid-base disorder entirely. It also guides whether to obtain additional studies such as a venous blood gas, lactate, ketones, toxicology testing, or an osmolar gap.
Calculating the Anion Gap
The typical anion gap formula is based on the major measured electrolytes: sodium, chloride, and bicarbonate. One common form is:
Anion gap = Sodium − (Chloride + Bicarbonate)
A few laboratories and references may also include potassium, but for emergency care, the sodium-based formula is the most common because it is easy, rapid, and widely available on the basic metabolic panel. The result reflects the amount of anion deficit from unmeasured ions.
For example: if sodium is 140, chloride is 104, and bicarbonate is 20, the calculation is 140 − (104 + 20) = 16. That value may be normal or mildly elevated depending on the lab reference range and the patient’s clinical context.
An anion gap calculator automates this diagnostic calculation, minimizing manual errors during time-sensitive critical care evaluation. It also helps clinicians easily assess sequential results from an electrolyte panel when monitoring a patient’s response to treatment.
Using the Anion Gap Calculator in urgent medicine
In acute care, the calculator is especially useful when a patient has sudden tachypnea, altered mental status, hypotension, vomiting, dehydration, or concern for toxicity. It is typically used alongside the basic metabolic panel, point-of-care testing, and sometimes blood gas analysis.
Rapid testing can provide immediate sodium, chloride, and bicarbonate values that allow clinicians to identify metabolic abnormalities early. This matters when the patient may be deteriorating and decisions about fluids, insulin, bicarbonate, antidotes, or dialysis need to be made without delay.
Practical use in the ER often follows this sequence:
- Examine the electrolyte panel and calculate the anion gap. Determine whether the patient has acidosis on a venous blood gas or arterial sample. Evaluate whether the pattern suggests increased anion gap metabolic acidosis or normal anion gap metabolic acidosis. Consider confirmatory tests such as lactate, beta-hydroxybutyrate, ketones, renal function, or toxicology studies.
The value of the calculator is not in isolation, but in the way it improves lab interpretation and supports early recognition of dangerous disease. In a busy ED workflow, it is one of the most efficient ways to screen for major acid-base pathology.
Normal, Elevated, and Reduced Anion Gap Findings
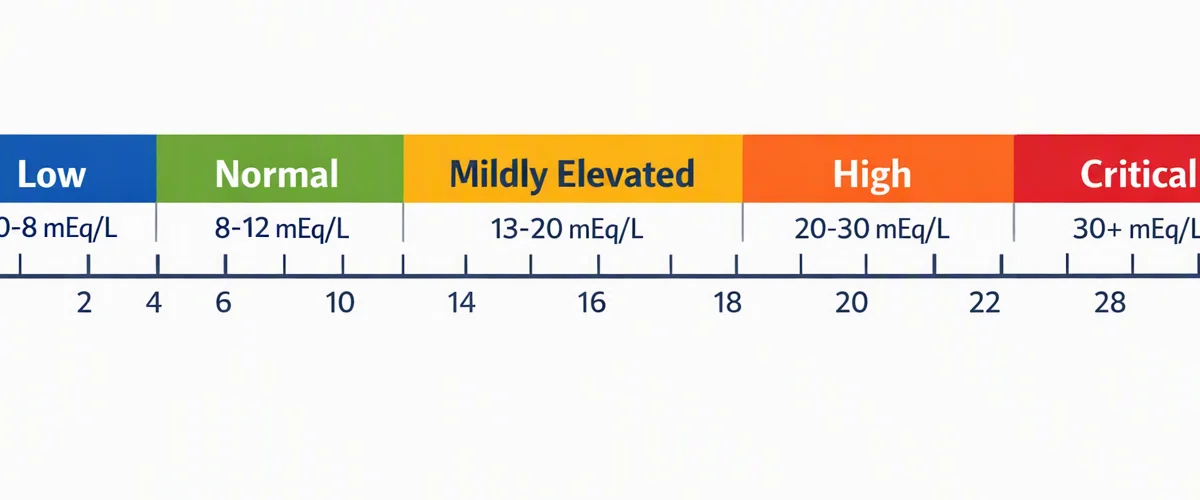
A standard anion gap usually suggests that any acidosis present is caused by reduced bicarbonate or chloride retention rather than by build-up of unmeasured acids. However, “normal” depends on the lab technique and comparison range, so clinicians should always interpret the value using site standards.
Increased anion gap metabolic acidosis suggests too much unmeasured acids in the blood. This is the result that often prompts urgent evaluation for lactic acidosis, ketotic acidosis, toxic alcohols, and renal failure. It is a key signal in metabolic evaluation when a patient appears unwell or has concerning vital signs.
A reduced anion gap is less common and can be ignored. It may occur with severe albumin deficiency, laboratory artifact, or occasionally other less common clinical conditions. Although a low value is not usually the main immediate problem, it should prompt reassessment of the test result and the broader acid-base disorder.
For practical interpretation, the anion gap should be seen as a pattern-recognition tool rather than a single diagnosis. https://anion-gap-app106.rivetgarden.com/posts/how-myeloma-impacts-the-anion-gap The presence of a normal or abnormal gap helps direct the next step in the evaluation algorithm, not replace it.
Frequent Causes of a High Anion Gap
Various conditions can result in high anion gap metabolic acidosis, and the emergency provider should prioritize rapid rule-out of serious causes. The key and most common include lactic acidosis, ketoacidosis, and use of toxic alcohols.
Lactic acidosis often develops in shock, hypoperfusion, seizures, severe infection, or tissue ischemia. In the ED, this is a major concern in patients with suspected sepsis, hypotension, or respiratory compromise. The anion gap may climb as lactate accumulates and uses up bicarbonate during buffering.
Ketoacidosis occurs when ketone bodies build up as organic acids. Diabetic ketoacidosis is the classic emergency presentation, but starvation or alcoholic ketosis can also contribute. The bicarbonate level often falls markedly, and the anion gap rises because ketones are unmeasured anions.
Toxic alcohols are another important cause of a high gap. Ethylene glycol and methanol are especially important because they can cause serious organ injury and may initially present with nonspecific symptoms. In these cases, the anion gap may increase later in the course, so timing matters. An elevated gap with suspicion of ingestion should prompt consideration of an osmolar gap and immediate toxicity screening.
Other causes may exist, but these three are the top priorities in the ED because they are time-sensitive and potentially reversible with early intervention.
Typical Causes of a Normal Anion Gap Acidosis
Normal anion gap acidosis is commonly associated with loss of bicarbonate or limited acid excretion. A typical lab pattern includes a decrease in bicarbonate with a compensatory increase in chloride, creating hyperchloremia-related acidosis.
Loose stools is a frequent cause. Intestinal bicarbonate loss can reduce serum bicarbonate while chloride rises to keep electrical balance. This is a classic example of how the chloride movement helps preserve balance on paper while the patient stays metabolically acidotic.
RTA is also an important cause. With this disorder, the kidneys fail to acidify the urine sufficiently or reclaim bicarbonate, leading to ongoing acidosis despite a normal anion gap. Identifying it matters because it may suggest chronic kidney disease or another underlying renal problem rather than a temporary illness.
Normal anion gap acidosis can also occur after large amounts of saline, though the main urgent causes to keep in mind remain gastrointestinal losses, RTA, and kidney bicarbonate loss. Reviewing fluids, medicines, and recent illness helps differentiate these causes.
In What Way Does Albumin Influence the anion gap
Albumin serves as the key not directly measured anion in plasma, so a low albumin level can spuriously reduce the anion gap. This is important because a patient may have a important acidosis that appears not as severe on the initial calculation.
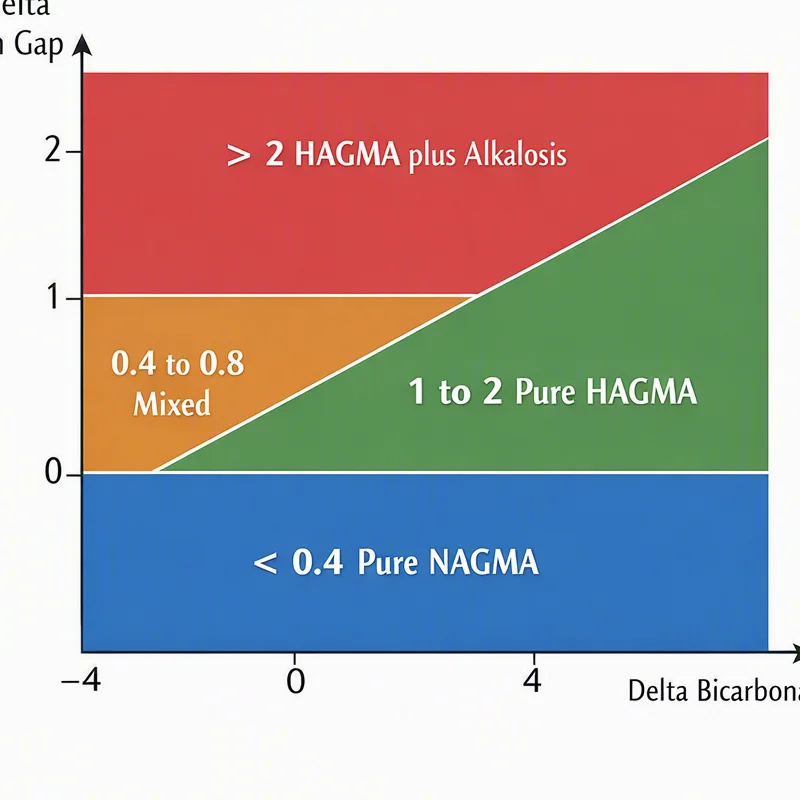
For this reason clinicians often use a anion gap correction when decreased albumin is present. A common approach is to adjust the measured gap upward when albumin is below normal, which helps uncover hidden excess acids. The exact correction method may vary by institution, but the principle is the same: low albumin can hide a dangerous elevation.
This adjustment is especially relevant in critical care and in patients with hepatic disease, malnutrition, inflammation, or chronic illness, where low albumin is frequent. Without correction, the anion gap may downplay the true degree of metabolic derangement.
In practice, a corrected calculation enhances lab interpretation and can reveal a masked high gap when the raw result appears misleadingly normal. That is one reason the anion gap calculator is most useful when paired with albumin data rather than used alone.
Systematic Interpretation in the ED
Reading the anion gap in the emergency department should use a clear approach. The goal is to identify the underlying acid-base disorder quickly and see whether immediate treatment is needed.
Step 1 — Confirm the chemistry values. Inspect sodium, chloride, and bicarbonate from the basic metabolic panel or point-of-care source. Make sure the result is credible and not obviously affected by laboratory error.
Step 2: Determine whether the patient has metabolic acidosis on a venous blood gas or other blood gas measurement. A low bicarbonate alone is not enough; pH and respiratory compensation help outline the full picture.
Then: Label the gap as normal, elevated, or low. If elevated, prioritize lactic acidosis, ketoacidosis, renal failure, and toxic alcohols. If normal, consider bicarbonate loss or chloride excess.
After that: If the presentation suggests ingestion, check the osmolar gap. An elevated osmolar gap with metabolic acidosis raises suspicion for toxic alcohol exposure, especially when clinical findings are unclear.
Finally: Combine all findings with the story. The same lab result means something different in a stable patient with mild diarrhea than in a hypotensive patient with altered mentation and respiratory distress.
This systematic method is essentially a bedside diagnostic algorithm that combines the calculator with patient status, blood gas data, and additional labs. It is a practical example of metabolic evaluation in real-time care.
Drawbacks and Problems of the Calculator
Like any diagnostic calculation, the anion gap calculator has limitations. Small differences in lab methods can create measurement variation, so the exact normal range can differ between institutions and analyzers.
Laboratory error can also mislead interpretation. Hemolysis, specimen handling issues, or inconsistent repeat values may produce a result that does not fit the clinical picture. When the number and the patient do not match, repeat testing and correlation with other data are essential.
The calculator does not replace the clinical context. A small increase may still be very important in an unstable patient with toxicity, while a larger value may be persistent or partially compensated in a patient with known kidney disease. The anion gap should thus be viewed as part of the whole clinical picture rather than as a single trigger.
Other common pitfalls include failing to account for albumin, assuming one cause explains every high gap, or failing to look for a mixed disorder. The most reliable interpretation usually comes from pairing the anion gap with blood gas findings, renal function, ketones, lactate, and toxin screening when indicated.
When to Escalate Evaluation or Treatment
Act promptly when the anion gap suggests a serious condition such as sepsis, renal failure, or poisoning. These are more than laboratory abnormalities; they are critical emergencies that can worsen quickly without treatment.
In suspected sepsis, an elevated gap plus elevated lactate or hemodynamic instability should lead to immediate resuscitation, cultures, antimicrobial therapy, and source evaluation. In renal failure, worsening acidosis may require nephrology input, close electrolyte monitoring, and possible renal replacement therapy depending on the overall picture.
For suspected poisoning, especially with toxic alcohols, ethylene glycol, or methanol, do not hold off for confirmatory results if the clinical suspicion is high. The combination of acidosis, elevated gap, and possible osmolar gap can support urgent antidotal therapy and consultation with toxicology.
Escalation is likewise appropriate when the patient has worsening mental status, respiratory fatigue, shock, or rapidly changing laboratory values. The calculator should guide the next action, not hold it up.
Frequently Asked Questions
What is the anion gap calculator used for?
The anion gap calculator is used to quickly estimate the anion gap from serum sodium, chloride, and bicarbonate values. In emergency medicine, it helps clinicians identify metabolic acidosis, differentiate acid-base disorders, and decide whether further evaluation for lactic acidosis, ketoacidosis, toxic alcohols, or renal failure is needed.
What’s the typical range for the anion gap?
The usual range depends on the measurement method and reference standard used by that lab. Because measurement techniques vary, clinicians should interpret the value using the facility’s range rather than relying on a one universal threshold. In practice, the result is best understood in combination with the patient’s symptoms, bicarbonate level, and overall acid-base balance.
How is a corrected anion gap for albumin?
To estimate a corrected anion gap, clinicians adjust the measured result upward when albumin is low because hypoalbuminemia can hide a true elevation. The exact correction formula can vary, but the goal is the same: account for the effect of low albumin on the gap so that significant metabolic acidosis is not missed. This is especially useful in patients with ongoing disease, liver disease, or critical illness.
What leads to a high anion gap in emergency medicine?
The most important causes of high anion gap metabolic acidosis in emergency medicine include lactic acidosis, ketoacidosis, and toxic alcohols such as ethylene glycol and methanol. Other important causes include sepsis and renal failure. The anion gap should be interpreted with blood gas results, lactate, ketones, renal studies, and the patient’s overall clinical picture.
When should an osmolar gap be checked with anion gap results?
An osmolar gap should be checked when there is concern for ingestion, especially if the patient has unexplained acidosis, altered mental status, or a history that suggests possible exposure to toxic alcohols. It is particularly useful when evaluating possible ethylene glycol or methanol poisoning. In the ED, the osmolar gap adds another layer of toxicity screening to the broader metabolic evaluation.